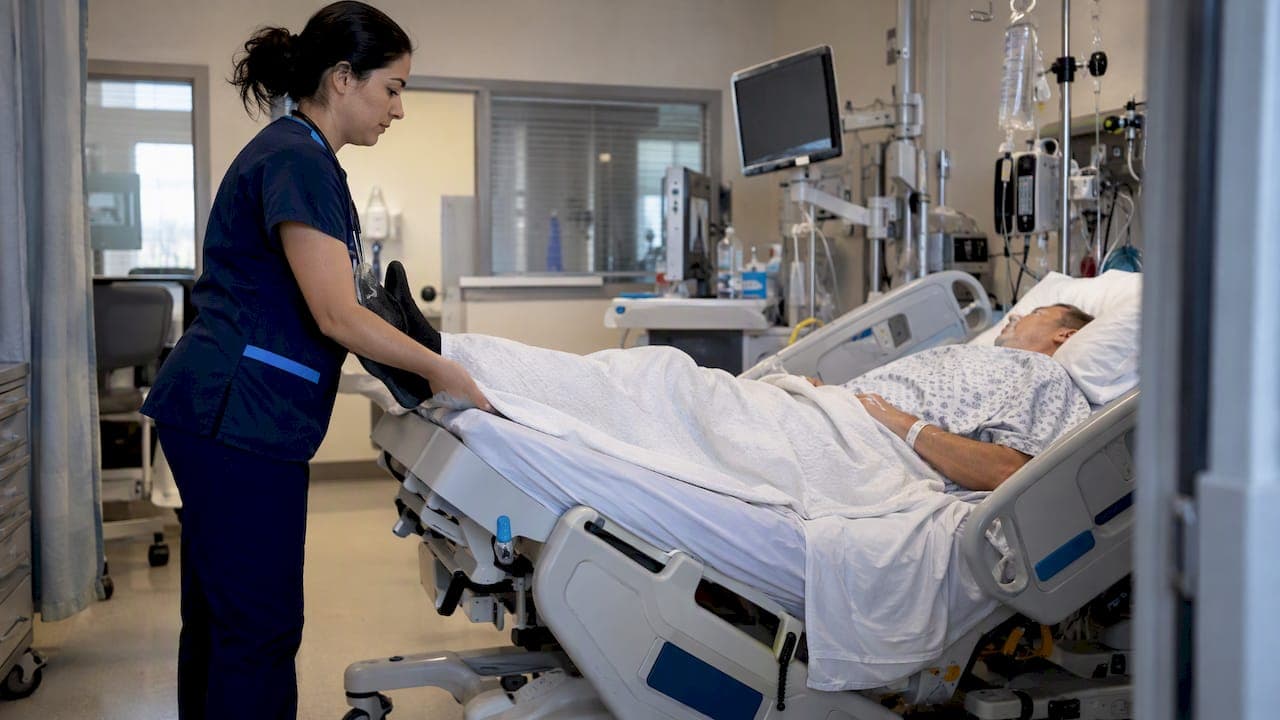
Hemodynamics measures pump, volume, and resistance. At the bedside, we focus on heart rate, mean arterial pressure (MAP), stroke volume or cardiac output trends, central venous pressure (CVP) or pulmonary capillary wedge pressure (PCWP) surrogates, and dynamic tests like passive leg raise to judge whether a patient will actually benefit from more fluid.
TL;DR:
- Use a passive leg raise, measuring stroke volume or cardiac output within one to two minutes; blood pressure alone cannot establish fluid responsiveness.
- Use PPV or SVV only with controlled ventilation, sinus rhythm, adequate tidal volume, and a closed chest; otherwise, choose passive leg raise testing.
- Echocardiography is the initial evaluation tool for undifferentiated shock; reserve pulmonary artery catheterization for complex or refractory cases requiring advanced data.
- Cardiogenic shock is supported by cardiac index at or below 2.2 L/min/m² with PCWP above 15 mm Hg and hypoperfusion; avoid reflexive fluid.
- A MAP near 65 mm Hg is a common perfusion target, but lactate, urine output, and extremity temperature can reveal shock despite normal pressure.
Table of Contents
- Core definitions: stroke volume, cardiac output, cardiac index, and MAP
- Preload, afterload, contractility, and the Frank-Starling law
- Invasive versus noninvasive monitoring: what each method actually shows you
- Static versus dynamic measures: predicting who actually needs fluid
- Calculating SVR, PVR, and reading PCWP correctly
- Reading shock types by their hemodynamic pattern
- Getting accurate readings: leveling, zeroing, and common errors
- What to memorize before your exam
- A nurse's take on learning hemodynamics
- Practice these concepts until they're automatic with RecallOS
- FAQ
- Sources
Core definitions: stroke volume, cardiac output, cardiac index, and MAP
Stroke volume (SV) is the amount of blood the left ventricle ejects in one beat, typically within a normal physiological range. Cardiac output (CO) is how much blood the heart pumps per minute, calculated as CO = heart rate × SV, with a typical resting range considered normal in clinical practice. Cardiac index (CI) adjusts CO for body size by dividing it by body surface area, allowing comparison across different body sizes, with normal values generally falling within a standard clinical range.
MAP represents the average pressure pushing blood through the arteries during a full cardiac cycle, calculated as MAP = (SBP + 2 × DBP) / 3. A MAP of at least 65 mm Hg is generally considered a reasonable target to help maintain adequate organ perfusion, particularly to vital organs like the kidneys and brain.
| Parameter | Normal range | What it tells you |
|---|---|---|
| Heart rate | Normal resting range | Pump frequency |
| Stroke volume | Typical physiological range | Pump efficiency per beat |
| Cardiac output | Typical physiological range | Total pump performance |
| Cardiac index | Typical values adjusted for body size | Pump performance scaled to body size |
| MAP | Clinical target range for perfusion | Perfusion pressure |
These five numbers are the backbone of every hemodynamic assessment you will chart, and every exam question that asks you to "calculate" something is almost always testing one of them.
Preload, afterload, contractility, and the Frank-Starling law
Three variables determine how much blood the heart pumps, and distinguishing them is what lets you pick the right intervention instead of guessing.
- Preload is the volume stretching the ventricle before contraction, estimated at the bedside using CVP for the right side and PCWP for the left side.
- Afterload is the resistance the heart pumps against, reflected in systemic vascular resistance (SVR) for the left ventricle and pulmonary vascular resistance (PVR) for the right.
- Contractility is the heart muscle's intrinsic squeeze, reflected in ejection fraction and influenced by inotropic drugs.
The Frank-Starling law states that, within limits, a more stretched ventricle contracts more forcefully, which is the physiological basis for giving fluid to raise preload and boost output. But the curve flattens and then drops: past a certain point, more volume overstretches the muscle fibers and cardiac output falls instead of rising, which is exactly why "more fluid" is not a universal fix and why fluid responsiveness testing matters more than a single CVP number.
In practice, a patient with low preload from hemorrhage needs volume, a patient with high afterload from severe hypertension may need a vasodilator, and a patient with poor contractility from heart failure often needs an inotrope rather than more fluid at all. Matching the physiology to the intervention, rather than treating every low blood pressure the same way, is the skill this section is really teaching.
Invasive versus noninvasive monitoring: what each method actually shows you
Different devices answer different questions, and knowing which one you are reading from changes how you interpret the number.
- Arterial line: continuous, beat-to-beat blood pressure and waveform, plus easy arterial blood gas access; it does not directly measure cardiac output.
- Central venous catheter: trends in CVP and central venous oxygen saturation (ScvO2), useful for tracking right-sided filling pressure and global oxygen balance over time rather than as a single absolute number.
- Pulmonary artery catheter (PAC): direct PCWP and cardiac output measurement, historically the gold standard, now reserved for complex or refractory shock because echocardiography is increasingly prioritized for initial evaluation of shock, with PAC use declining and now targeted to refractory or complex cases.
- Echocardiography: a noninvasive, repeatable snapshot of ventricular filling, contractility, and valve function that has become the first-line tool for evaluating undifferentiated shock.
- Noninvasive CO monitors (pulse contour and waveform analysis): useful for trending changes in cardiac output, though these methods are approximations that require calibration and are sensitive to shifts in vascular tone.
If a patient's shock picture is not explained by the bedside exam and initial echo, or if they are not responding to first-line therapy as expected, that is the point to loop in critical care or cardiology for consideration of PAC placement or advanced monitoring, rather than relying on escalating guesswork from the bedside alone.
Static versus dynamic measures: predicting who actually needs fluid
A single CVP number is a weak predictor of whether a patient will respond to fluid, because CVP's absolute value poorly predicts fluid responsiveness and its usefulness comes mainly from trend and waveform interpretation with correct transducer leveling. This is why current practice leans on dynamic measures instead. The Surviving Sepsis Campaign recommends using dynamic measures, such as the response to a passive leg raise or a fluid bolus measured by stroke volume or pulse pressure variation, rather than static measurements when guiding fluid resuscitation in sepsis or septic shock.
- Position the patient semi-recumbent, then raise the legs to 45 degrees while lowering the head to supine, which auto-transfuses roughly 300 mL of venous blood toward the heart.
- Measure stroke volume or cardiac output (not just blood pressure) before and after the maneuver, within about one to two minutes.
- A meaningful rise in SV or CO suggests the patient is fluid responsive and likely to benefit from a bolus.
Pulse pressure variation (PPV) and stroke volume variation (SVV) work on a similar principle but need specific conditions to be valid: the patient must be on controlled mechanical ventilation with adequate tidal volume, in sinus rhythm, with a closed chest. These tests lose reliability in spontaneously breathing patients, those with arrhythmias, right ventricular failure, or an open abdomen, which is a common trap in both practice and exam questions.
Pro Tip: If PPV or SVV prerequisites aren't met, default to a passive leg raise with direct SV or CO measurement instead of trusting the number.
Calculating SVR, PVR, and reading PCWP correctly
Vascular resistance calculations show up constantly in critical care nursing, and the formulas share a structure worth memorizing together.
| Parameter | Formula | Normal range |
|---|---|---|
| SVR | (MAP − CVP) ÷ CO × 80 | Roughly 800 to 1200 dynes·s·cm⁻⁵ |
| PVR | (mean PAP − PCWP) ÷ CO × 80 | Usually under approximately 250 dynes·s·cm⁻⁵ |
Both formulas use the same × 80 conversion factor to express resistance in dynes·s·cm⁻⁵, and both divide a pressure difference by flow, which is the same logic as calculating electrical resistance from voltage and current.
PCWP, obtained via a wedged pulmonary artery catheter, serves as a surrogate for left atrial pressure and therefore left ventricular preload. Readings should be taken at end-expiration to avoid artifact from intrathoracic pressure swings, which matters even more in mechanically ventilated patients where positive pressure can falsely elevate the number. When a single reading looks inconsistent with the clinical picture, average several respiratory cycles or repeat the measurement rather than charting an outlier value as fact.

Reading shock types by their hemodynamic pattern
Each shock type produces a distinct combination of preload, pump function, and resistance, and recognizing the pattern is faster than memorizing isolated numbers.
- Hypovolemic shock: low CVP, low PCWP, low CO, and high SVR as the body clamps down. Nursing priority is rapid volume assessment, serial vital signs, and identifying the source of loss.
- Cardiogenic shock: elevated PCWP with low CO and CI, often defined by a CI at or below 2.2 L/min/m² with PCWP above 15 mm Hg alongside signs of hypoperfusion. Nursing priority is careful fluid restriction, monitoring for pulmonary edema, and readiness for inotropic support.
- Distributive shock (septic, anaphylactic, neurogenic): low SVR with normal or elevated CO initially. Nursing priority is early fluid resuscitation guided by dynamic measures and close monitoring for the shift toward myocardial depression later in sepsis.
- Obstructive shock (tamponade, massive pulmonary embolism, tension pneumothorax): elevated CVP with low CO from a mechanical barrier to filling or ejection. Nursing priority is rapid recognition of the underlying obstruction since this category often needs a procedural fix rather than fluids or drugs alone.
Mixed pictures happen too. An unexpectedly low SVR in a patient presumed to be in cardiogenic shock can signal a combined pathology that warrants reassessing the whole treatment plan. Blood pressure alone can also be misleading, since normotensive cardiogenic shock exists and perfusion markers like lactate, urine output, and extremity temperature can reveal inadequate perfusion even when the numbers on the monitor look reassuring. Trending these markers over time, rather than anchoring on one measurement, is what catches deterioration early enough to act. For a deeper dive into applying these patterns under exam conditions, our CCRN hemodynamics review walks through scenario-based practice.
Getting accurate readings: leveling, zeroing, and common errors
Every invasive pressure reading depends on correct setup, and small technical errors produce numbers that look precise but are simply wrong.
The transducer must be leveled at the phlebostatic axis, the point at the fourth intercostal space, midway between the anterior and posterior chest wall, because even small vertical deviations in transducer level cause clinically significant inaccuracies in CVP and arterial pressure readings. Re-zero the transducer to atmospheric pressure after any change in patient position, and read pressures at end-expiration to avoid the influence of intrathoracic pressure swings, averaging several respiratory cycles in ventilated patients rather than trusting one data point.
- A damped arterial waveform (sluggish, rounded, losing its sharp upstroke) usually signals a clot, kink, or air bubble in the line rather than a true physiologic change.
- Before escalating a suspicious reading, flush the line, check all tubing connections, confirm the transducer is at the correct level, and re-zero.
- If a blood draw from an arterial or central line looks off or the site shows signs of complication, follow proper technique for recognizing blood draw complications before trusting the sample.
Pro Tip: Always re-level and re-zero after repositioning a patient, since a line that reads perfectly in one position can read falsely high or low in another.
What to memorize before your exam
A short list of facts covers most hemodynamics questions on nursing and certification exams.
- MAP = (SBP + 2 × DBP) / 3, with a target around 65 mm Hg for most critically ill adults.
- CO = HR × SV, and CI = CO divided by body surface area.
- A positive passive leg raise means a meaningful rise in stroke volume or cardiac output, not blood pressure alone.
- SVR and PVR both use the × 80 conversion factor and follow the same pressure-difference-over-flow logic.
Spaced retrieval practice, where you re-test yourself on these formulas days apart instead of cramming once, builds the kind of recall that holds up under exam pressure. Pairing that with scenario-based questions and time at a simulation monitor, where you practice reading real waveforms instead of just numbers on a page, closes the gap between knowing the formula and applying it at the bedside.
A nurse's take on learning hemodynamics
The numbers on a monitor are a starting point, not a verdict. I have seen students treat a single CVP reading or one blood pressure value as the whole story, when the patient in front of them was already telling a different one through color, mental status, or urine output.
Learn the formulas cold, but learn to distrust any single number more than you trust it. Dynamic testing exists because static numbers lie often enough to matter, and the same should be true of your own bedside habits: trend the data, recheck your technique before you believe an alarming value, and practice reading waveforms on a simulator until a damped line or a bad baseline jumps out at you instantly. That instinct is what separates someone who memorized hemodynamics from someone who can use it.
— Caleb
Practice these concepts until they're automatic with RecallOS
Hemodynamics is one of those topics where you either know the formulas cold under pressure or you fumble them on exam day, and the difference comes down to how you practiced, not how many hours you spent reading. We built a study app around daily, high-yield practice questions so you drill the exact calculations and shock patterns covered here instead of sifting through generic trivia.
Our Daily Recall Run targets weak spots automatically and tracks your progress with streaks, so a concept like PCWP interpretation or SVR calculation keeps resurfacing until it sticks. If you would rather turn your own class notes or a hemodynamics study guide into custom quiz questions, you can upload your notes directly. Explore Recall+ and Recall Pro to find the plan that fits your exam timeline.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
FAQ
What are the basic principles of hemodynamics?
Hemodynamics rests on three interacting variables: preload (volume returning to the heart), afterload (resistance the heart pumps against), and contractility (the heart's intrinsic pumping strength). Together these determine stroke volume and cardiac output, which in turn set the blood pressure and organ perfusion we monitor at the bedside.
What is a bad cardiac output number?
A cardiac index at or below 2.2 L/min/m² generally signals inadequate pump function, a pattern commonly seen in cardiogenic shock. The exact threshold that matters clinically depends on the patient's baseline and accompanying signs of hypoperfusion, like lactate and urine output, rather than the number alone.
What are the 7 steps of blood flow?
A common way to sequence systemic blood flow is: right atrium, right ventricle, pulmonary artery, lungs for oxygenation, pulmonary veins, left atrium, and left ventricle before blood is ejected into systemic circulation. Nursing hemodynamic monitoring tracks this circuit indirectly through pressures like CVP (right-sided filling) and PCWP (left-sided filling).
What are the basic components of hemodynamic monitoring?
Core components include an arterial line for continuous blood pressure and waveform, a central venous catheter for CVP and oxygen saturation trends, and in selected cases a pulmonary artery catheter or echocardiography for direct cardiac output and filling pressure data. Noninvasive pulse contour monitors can estimate cardiac output trends as a less invasive option when continuous invasive monitoring is not warranted.
Why do nurses use dynamic measures instead of just CVP?
Static measurements like CVP correlate poorly with whether a patient will actually benefit from more fluid, which is why the Surviving Sepsis Campaign guidelines favor dynamic measures such as passive leg raise testing or pulse pressure variation. These dynamic tests directly show whether stroke volume rises in response to added volume, which is the question that actually matters for fluid decisions.
Sources
- Surviving Sepsis Campaign: International guidelines for management of sepsis and septic shock (2026)
- Effective hemodynamic monitoring - PMC - NIH
- Calculation of pulmonary and systemic vascular resistance - OpenAnesthesia